Session-by-Session Protocol: CBT for Depression
A session-by-session protocol for individual cognitive behavioural therapy for depression over roughly sixteen to twenty sessions, following Beck's cognitive therapy with behavioural activation in the early phase: overview and evidence, assessment, phase-by-phase aims and tasks, measures, adaptations, and relapse prevention.
About this resource
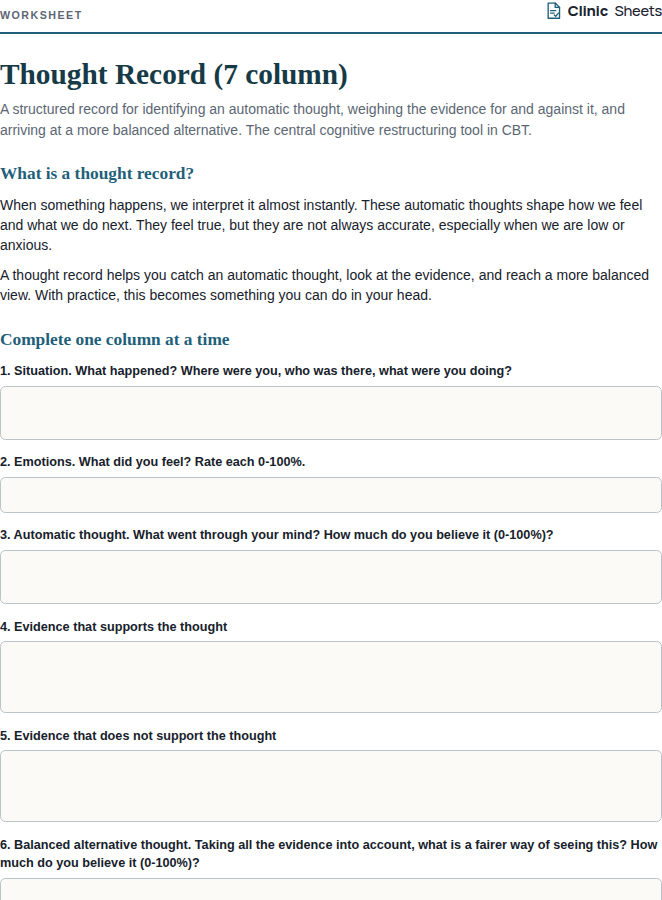
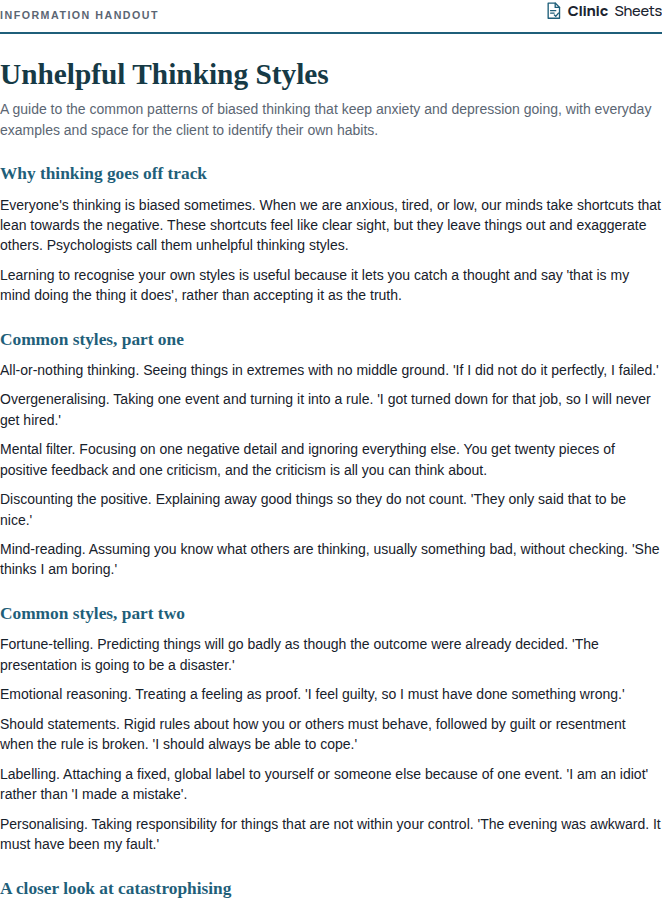
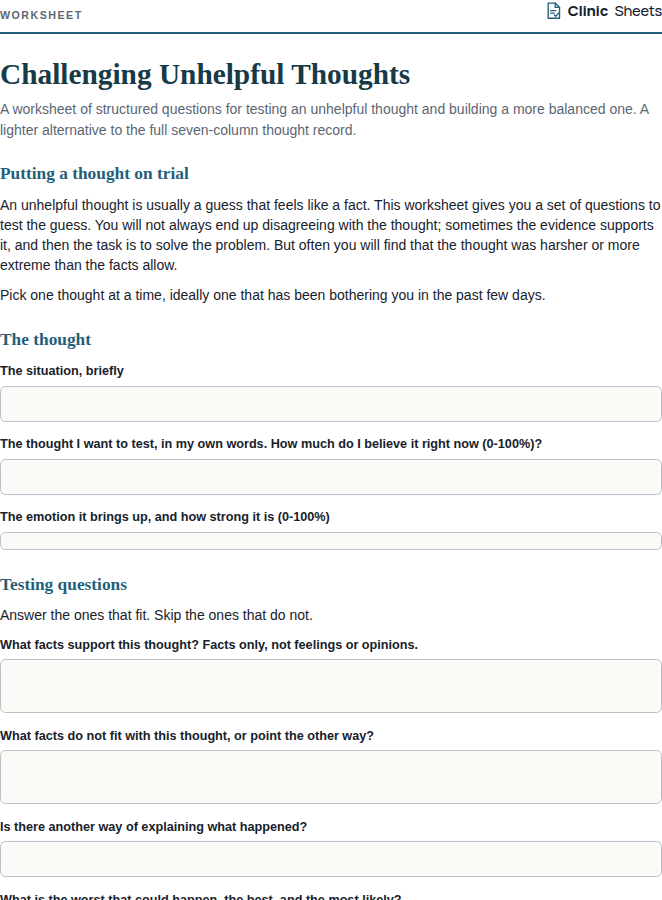
Cognitive therapy for depression, described by Beck, Rush, Shaw and Emery in 1979 and updated by Judith Beck, remains the reference protocol for psychological treatment of depression. It proceeds in a recognisable order: socialising the client to the cognitive model and structured sessions, activating behaviour early to produce some relief and generate data, teaching the client to identify and evaluate negative automatic thoughts, working on the underlying assumptions and core beliefs that make the person vulnerable, and ending with explicit relapse prevention. Trials comparing cognitive therapy with antidepressant medication, including DeRubeis and colleagues' trial in moderate to severe depression, and the Dimidjian trial that established behavioural activation as an effective treatment in its own right, together support the sequence used here: behavioural work first, cognitive work built on it.
This protocol sets out the treatment in phases with a session range for each, because the pace depends on severity, and specifies the aims, in-session tasks, between-session tasks and measures for each phase. Every session uses the same structure described by Judith Beck: brief mood check with the measure, bridge from the last session, agenda setting, review of between-session work, work on agenda items with periodic summaries, setting new between-session work, and a final summary and feedback.
The professional version is the full protocol, with sections on assessment and suitability, adapting the protocol to severity, comorbidity and setting, and relapse prevention and ending. It assumes the clinician is trained in CBT and has access to supervision.
How to use it
- Complete a full assessment in the first one or two sessions, including diagnosis, severity on the PHQ-9 or BDI-II, risk, history of episodes, comorbidity, medication and previous treatment. Agree the number of sessions and the plan for measuring progress.
- Administer the PHQ-9 or BDI-II at every session and review the score with the client. Follow up any endorsement of the suicide item the same session and document the risk assessment and plan.
- Keep the session structure from session 1 onward. The structure is not a formality; it teaches the client the skills of focusing, prioritising and reviewing that depression erodes.
- Set between-session work in every session, write it down, anticipate obstacles, and review it at the start of the next session. Work not done is discussed, not skipped.
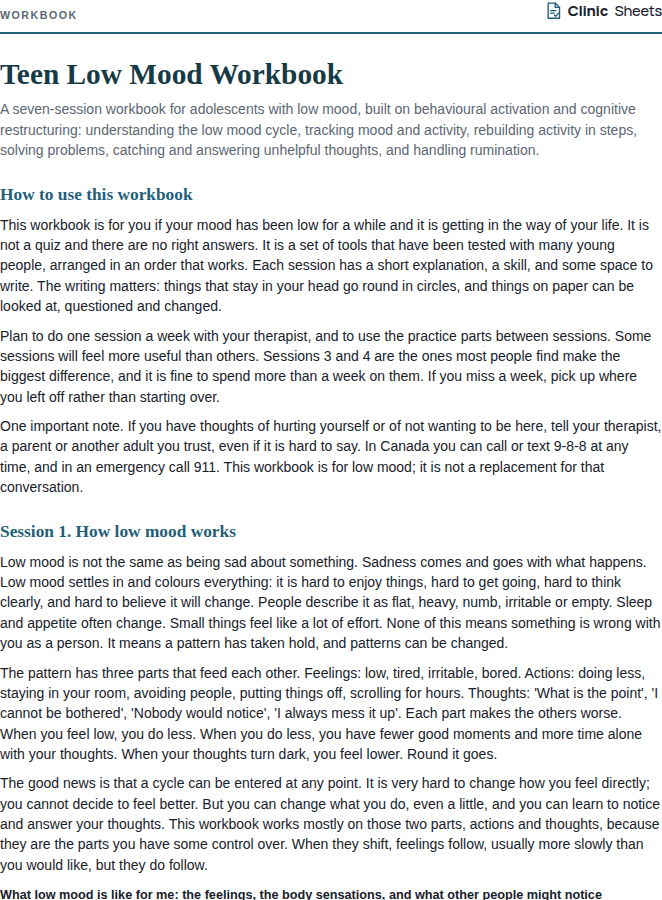
- Move through the phases in order but at the client's pace. A severely depressed client may spend eight sessions on activation before any thought record; a mildly depressed, psychologically minded client may reach cognitive work by session 3.
- Plan the ending from the middle of treatment. Space the last sessions to fortnightly or monthly, complete a written relapse prevention plan, and offer booster sessions.
References
- Beck, A. T., Rush, A. J., Shaw, B. F., & Emery, G. (1979). Cognitive Therapy of Depression. Guilford Press.
- Beck, J. S. (2020). Cognitive Behavior Therapy: Basics and Beyond (3rd ed.). Guilford Press.
- DeRubeis, R. J., Hollon, S. D., Amsterdam, J. D., Shelton, R. C., Young, P. R., Salomon, R. M., O'Reardon, J. P., Lovett, M. L., Gladis, M. M., Brown, L. L., & Gallop, R. (2005). Cognitive therapy vs medications in the treatment of moderate to severe depression. Archives of General Psychiatry, 62(4), 409-416.
- Dimidjian, S., Hollon, S. D., Dobson, K. S., Schmaling, K. B., Kohlenberg, R. J., Addis, M. E., Gallop, R., McGlinchey, J. B., Markley, D. K., Gollan, J. K., Atkins, D. C., Dunner, D. L., & Jacobson, N. S. (2006). Randomized trial of behavioral activation, cognitive therapy, and antidepressant medication in the acute treatment of adults with major depression. Journal of Consulting and Clinical Psychology, 74(4), 658-670.